My quest for understanding intermolar width—often shortened to IMW—began when I started digging deeper into airway science and craniofacial development.
I came across the work of Dr. Kevin Boyd, a pediatric dentist in Chicago specializing in children under age seven with a background in anthropology. He was one of the first subject-matter experts I encountered who discussed early jaw expansion and the importance of helping children remain nasal breathers for life.

A Conversation With Dr. Kevin Boyd
During one of Dr. Boyd’s podcasts or webinars, he mentioned that people with questions could email him.
In March 2022, I asked whether children who received appropriate early intervention could develop an intermolar width of 45–50 millimeters and have enough room for their wisdom teeth to erupt.
He replied and invited me to call him while he was traveling. Jackpot.
We spoke about early treatment, wisdom teeth, dental-arch development, and intermolar width.
Dr. Boyd explained that children treated earlier and appropriately may experience partial or complete eruption of their third molars, although they do not always erupt in perfect alignment. Fully erupted and aligned third molars are not necessarily a success criterion for his protocol. However, if extraction is eventually needed, partially or fully erupted teeth may be easier to remove than fully impacted teeth.
He also discussed research associated with James McNamara and the concept that approximately 40 millimeters—measured between the upper first molars near the gingival margins—may provide sufficient width for function and aesthetics in many cases.
Intermolar width is one piece of a larger clinical picture. A single measurement should not be used to diagnose an airway, orthodontic, breathing, or sleep condition.
The Bogue Index
We also discussed Edward Bogue, a dentist from the late 1800s who studied dental arches, nasal breathing, malocclusion, and development in young children.
Dr. Boyd developed what he calls the Bogue Index as a simple way to discuss maxillary transverse development.
For example, the corresponding index value for a seven-year-old would be 31 millimeters.
24 millimeters + the child’s chronological age
The Bogue Index is an index—not a diagnostic test. It does not diagnose obstructive sleep apnea, malocclusion, or another medical condition. It may be used by qualified professionals as one screening measurement alongside validated clinical assessments.
What I Started Noticing
After that conversation, I started paying closer attention to intermolar width among people I knew—children, professional athletes, parents, and grandparents.
I also began asking adults about breathing, sleep, allergies, mouth breathing, asthma, and other health experiences while comparing those experiences with measurements associated with the width of the palate.
What stood out to me was how many people reported that they did not sleep well but had learned to suffer in silence.
Some feared being told they needed a CPAP machine or surgery. Others had lived with allergies, asthma, mouth breathing, poor sleep, or chronic congestion for so long that those experiences felt normal.
Many felt that the medical system offered a long line of medications and procedures without helping them understand the complete picture.
The Plumbing Analogy
Many people have small jaws, high-arched palates, and less available space within the oral and nasal structures.
I often describe the body using an engine-and-plumbing analogy.
A person’s body may place large demands on an airway system that does not have enough capacity to perform comfortably under those demands.
That may show up through restless sleep, waking unrefreshed, nasal congestion, mouth breathing, or labored nighttime breathing.
Upper Airway Resistance Syndrome—UARS—is one condition discussed within sleep medicine. Someone may not wake up choking or snore loudly, but they may still experience increased breathing effort while sleeping.
Only qualified professionals can evaluate whether symptoms are related to UARS, obstructive sleep apnea, nasal obstruction, allergies, craniofacial development, or another cause.
A Jetta in a League of Lamborghinis
Imagine asking a stock Volkswagen Jetta to race against a group of Lamborghinis for an entire season.
After several races, the Jetta’s engine fails.
You bring it to a performance shop and explain that it has been competing in 50-mile races against Lamborghinis every week.
The mechanic would immediately understand that the demands being placed on the car exceeded its available capacity.
That analogy reflects the question I keep asking about the human airway:
Is the developing system being given enough structural capacity to handle the demands placed upon it?
How Is Intermolar Width Measured?
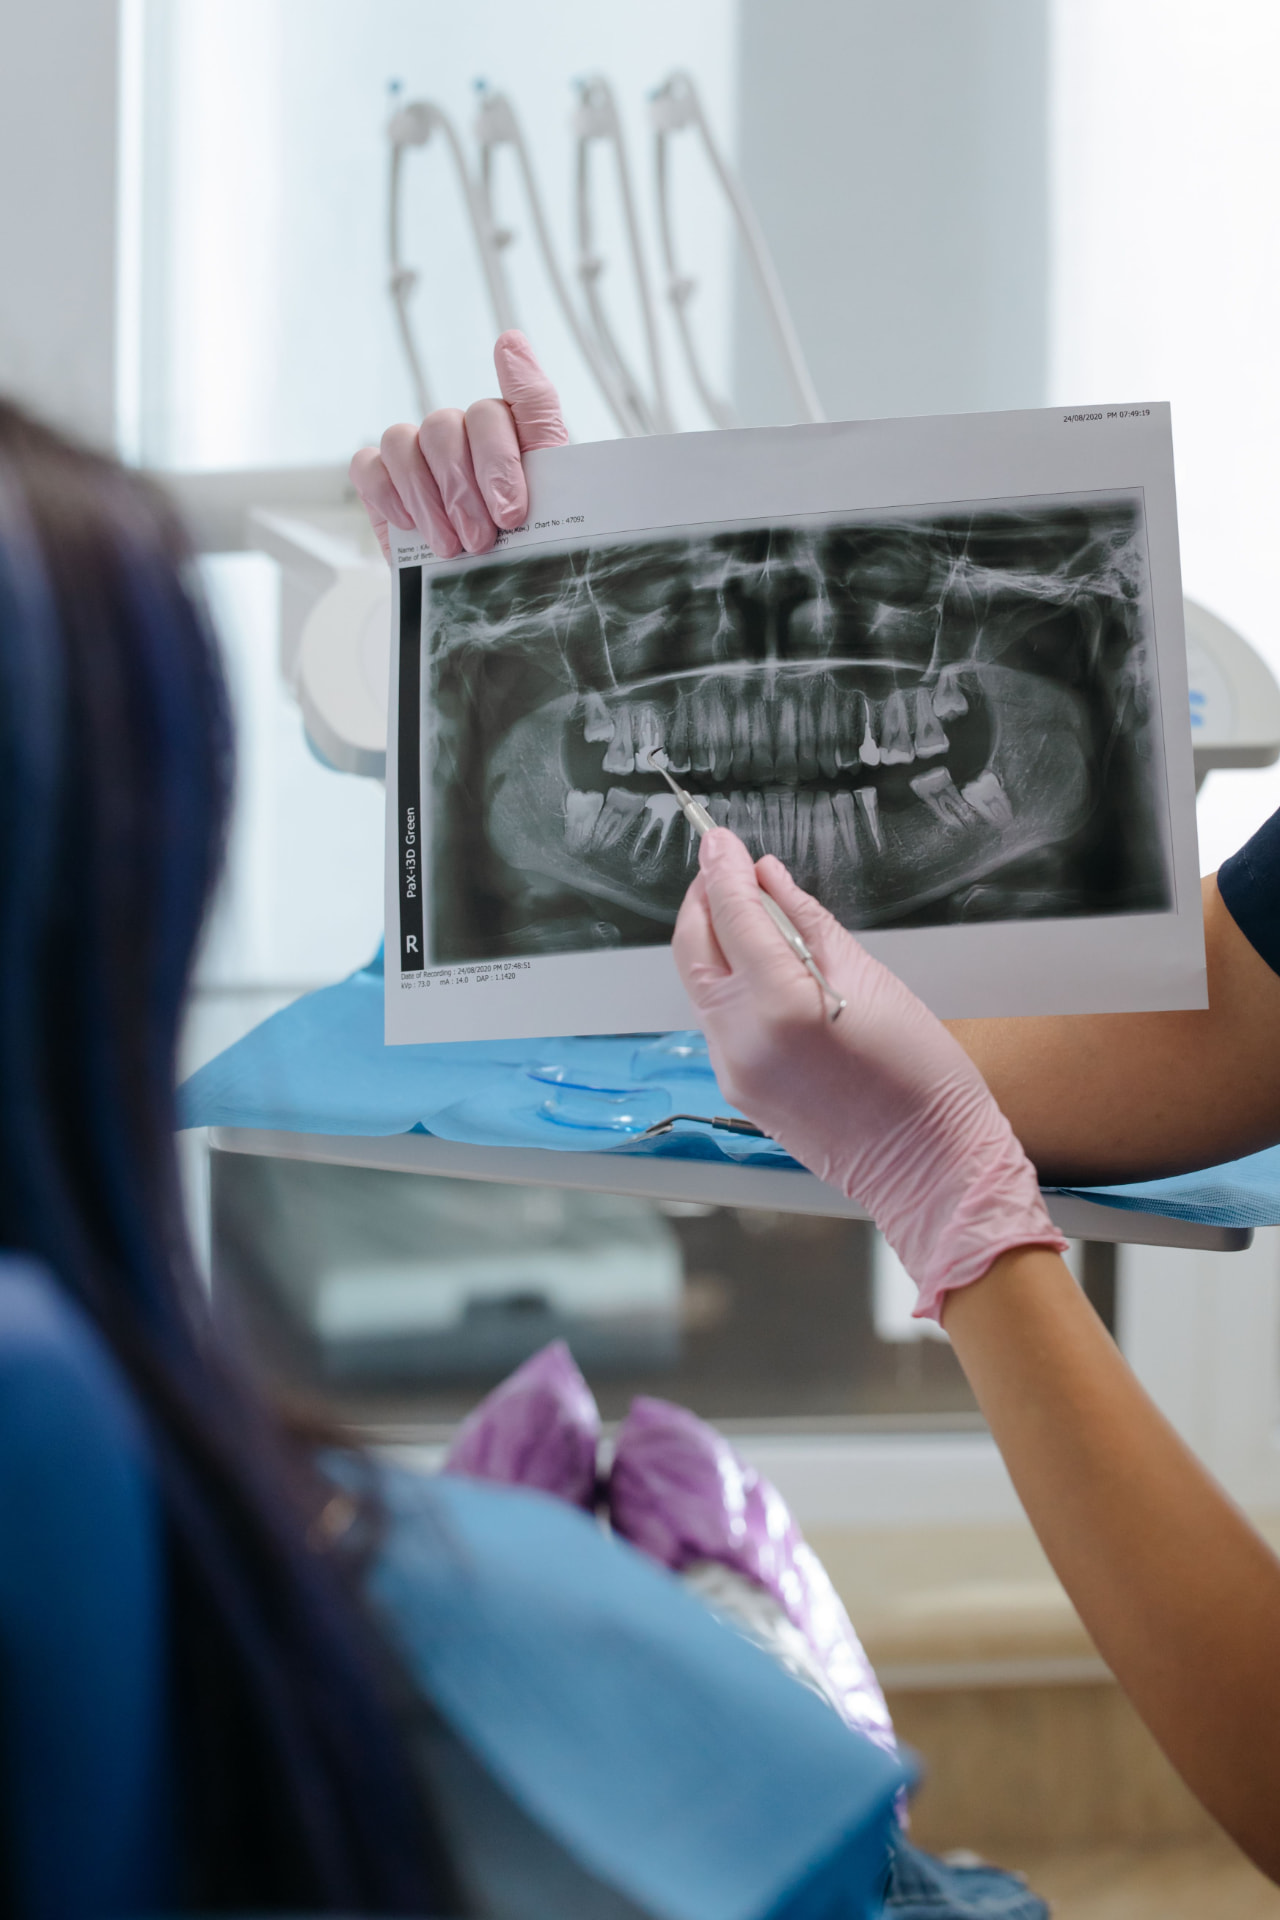
Intermolar width refers to the distance between corresponding molars across the upper dental arch.
A dentist or orthodontic professional can measure it using clinical models, digital scans, or other appropriate tools.
Parents interested in their child’s dental-arch development can ask a qualified dentist, orthodontist, or airway-focused professional whether intermolar-width measurement is appropriate and how it should be interpreted alongside the child’s age, symptoms, growth, and complete clinical evaluation.
Because the roof of the mouth also forms the floor of the nose, the dimensions of the palate are one part of the broader conversation about oral space, tongue posture, nasal breathing, and craniofacial development.
Intermolar width does not tell the entire story, but it can give parents and qualified professionals another question to explore.